
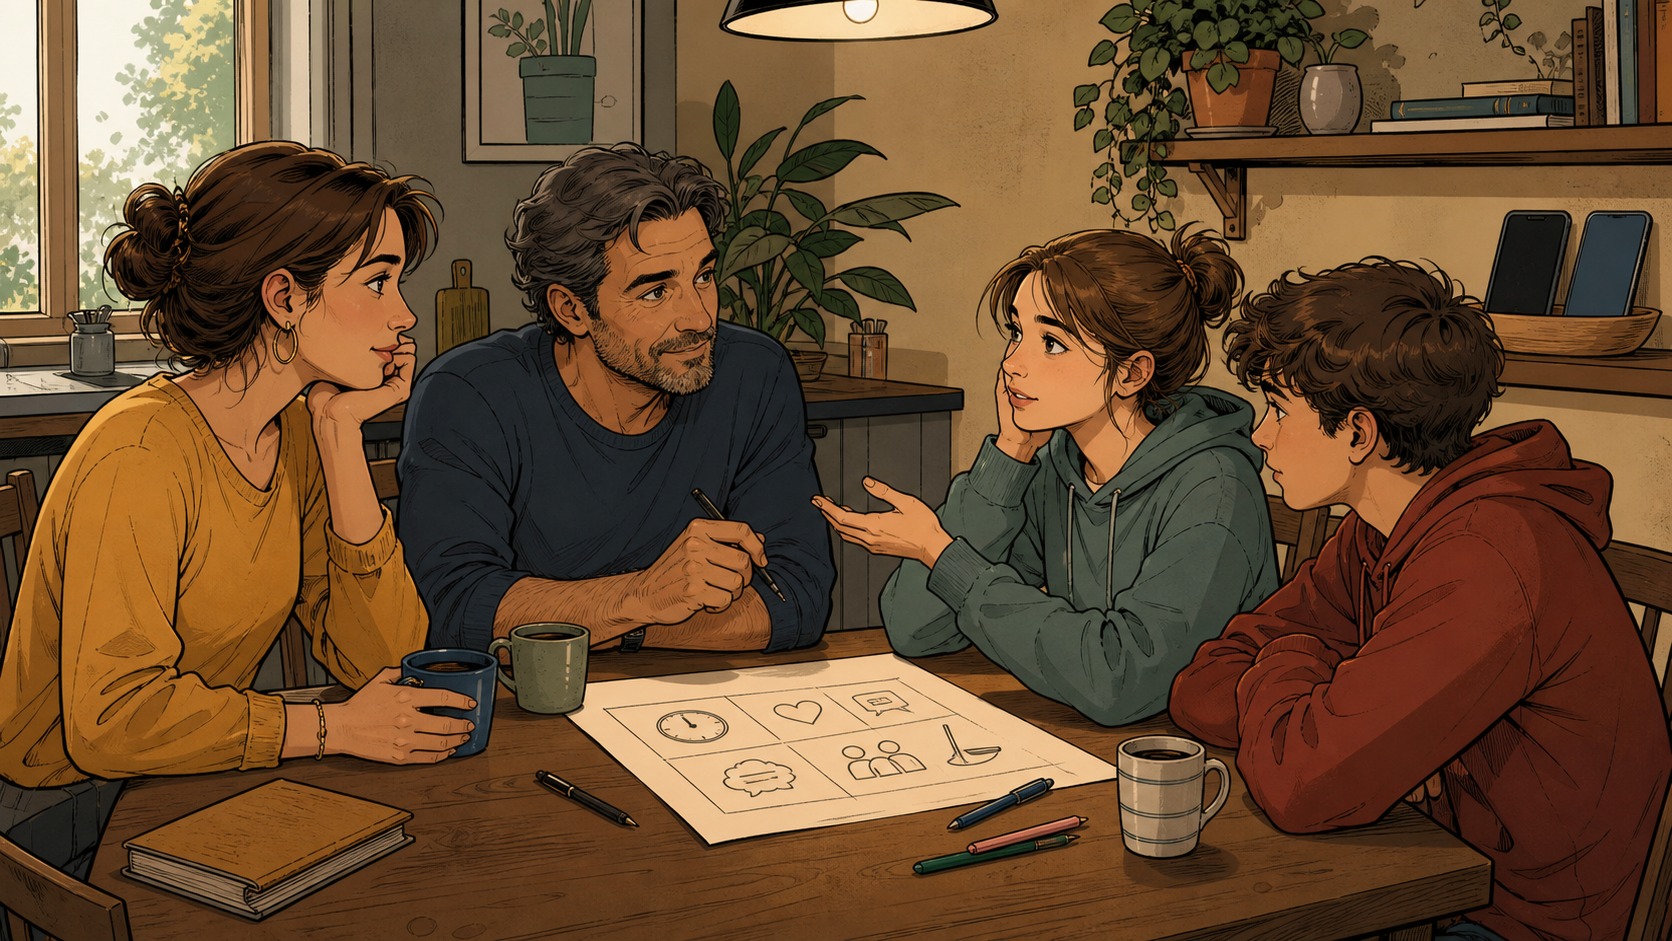
Crying cannot be scheduled, but the environment that receives it can be prepared. Before a difficult stretch, a family can decide how transitions will happen, what sound level will be held, how feeding will be offered without becoming pressure, which small choices will stay available, and how an imperfect response will be repaired. These five decisions do not promise silence or replace clinical assessment. They create a practical setting in which dysregulation brings fewer surprises, fewer competing adults and more safety.
A crisis begins before the first cry#
When an infant or young child becomes distressed, adults often search the visible minute for the explanation: hunger, fatigue, pain, frustration or stimulation. Yet the ground may already have been shaped by abrupt changes, overlapping noise, contagious rushing, or adults who have not decided who will take over. Preparing the environment means reducing the number of decisions that must be invented with a flooded nervous system.
The UNICEF overview of why babies cry notes that needs can overlap. That is why a fast explanation rarely settles the whole picture. A prepared household can observe breathing, color, responsiveness, feeding and a change from the usual pattern. If a warning sign is present, use local clinical support; no home plan should delay that choice.
Decision 1: make transitions named and gradual#
Transitions are the small bridges between play and bath, outside and home, arms and crib, one caregiver and another. Rather than moving a child abruptly, an adult can name what is coming, offer a minute of closure, and keep two cues stable: the same light, a short song, a familiar walking route, or the same sequence. Predictability is not rigidity. It gives a body a recognizable clue while it is still changing gears.
The advance decision identifies the most fragile transition and sets up relief. If arriving home coincides with cooking and messages, one adult is available before overload starts. That concrete choice protects more than a promise to be patient. It also lets a tired caregiver say “I need two minutes” before holding, rather than discovering the limit after their body has become tight.
Decision 2: design sound instead of chasing silence#
Designing sound does not turn a home into a library. It distinguishes one guiding voice from three competing voices, a predictable household sound from repeated startling noise, and a useful pause from abandonment. Before a difficult period, adults can decide which devices go off, where conversation happens, and what signal asks everyone to lower volume.
Preparation does not remove crying; it stops the environment from creating a second crisis.
The guiding idea is simple: Preparation does not remove crying; it stops the environment from creating a second crisis.
The American Academy of Pediatrics offers gentle soothing strategies and recommends a safe break when an adult is overwhelmed. A low voice, brief sentences and steady movement usually give more information than switching every few seconds among music, walking and toys. If an infant sleeps, safe-sleep guidance remains in force; soothing never makes an unsafe surface or position safe.
Decision 3: treat feeding as a meeting, not a switch#
Feeding becomes confusing when it is used to solve every protest. Preparation means deciding where it will be offered, which cues will be watched, who understands the established feeding plan, and what the family will do if the baby pulls away, coughs, seems uncomfortable, or repeatedly refuses. Offering a feed may be appropriate; pushing without reading cues can add pressure and hide a difficulty that deserves review.
A useful agreement does not prescribe quantities or remedies. It says that feeding follows cues, positioning stays safe, and repeated functional changes are noted. Poor feeding, unusual breathing, lethargy or a marked change calls for clinical advice. The World Health Organization guidance for newborn care keeps general condition above a reassuring home explanation.
Decision 4: keep small choices where they fit#
During dysregulation, ten questions create more load. But removing every choice can intensify a child’s loss of control. Preparation selects two real, safe options: held or accompanied on the floor, short book or song, blue cup or green cup, walk by the door or sit in the calm corner. Offer one choice at a time, without turning it into a test.
Choices do not negotiate safety boundaries or demand that crying stop. They are a route to participation when language is limited. If no answer comes, the adult chooses calmly and explains: “This is too much right now; I will choose and stay close.” Autonomy and comfort can then work together instead of competing.
Decision 5: agree on repair before the mistake#
No adult responds well every time. A caregiver may raise their voice, insist on an activity, misread a cue, or wait too long to seek relief. Prepared repair does not make the error unimportant; it prevents shame from extending it. It means stopping, securing bodies, naming what happened in simple words, changing the action, and returning later to the plan with the other caregiver.
Repair also has a safety threshold. If an adult notices clenched teeth, rigid hands, an urge to shake, or fear of losing control, they place the baby on the back in a firm empty safe-sleep space and call for help. The CDC warns that abusive head trauma is preventable and that frustration with crying can be a factor. Relief is care, not moral withdrawal.
Case 1: arriving home stops being an ambush#
Two-year-old Leo arrived from child care hungry and tired. At home, adults asked about dinner while the television played and two people talked about work. He cried, threw objects, and dinner was delayed. The family did not look for a compliance trick. They chose a transition: snack ready, television off, one question between two options, and ten minutes of accompanied floor time before cooking.
During the first week, crying did not vanish. Leo began pointing to the cushion and accepted sitting with his mother before choosing. The useful measure was not instant quiet; it was fewer simultaneous decisions and a clearer recovery. When fever and lethargy appeared one day, the family left the script and sought advice. A prepared environment does not replace medical care.
Case 2: a difficult feed stops accumulating experiments#
Three-month-old Mara protested midway through several feeds. Each adult changed position, pace and nipple type at the same time. Their new agreement was simple: one person offers the feed; the other briefly records coughing, pauses, diapers and recovery; no new variable is added until there has been time to observe. After three repeated days, they requested a feeding assessment rather than continuing to search for products.
The appointment allowed technique and cues to be reviewed with concrete information. Preparing feeding is not guessing a diagnosis; it is protecting observation. The NHS page on soothing a crying baby encourages families to seek support when crying is worrying or exceeds their resources. A useful note opens a clinical conversation; a cascade of experiments often closes it.
Case 3: repairing after a hard afternoon#
After a fragmented night, Ivan raised his voice when his four-year-old refused a coat. She shouted louder and he felt he had to force speed. He remembered the family agreement: lower sound first, then offer one safe choice, and repair if the response fails. He stepped back, said that his voice had been frightening, put two coats on a chair, and asked his partner to take over departure for five minutes.
Later they did not deliver a long lesson. Ivan explained that they would practice the transition with more time and asked what signal she could use when she needed a pause. Repair did not erase the rush, but it kept the scene from defining the relationship. Persistent irritability, exhaustion or fear of causing harm calls for a larger support network and professional help, not isolated willpower.
A card to review every week#
The card can ask five questions: Which transition will we anticipate? Which sound will we reduce? How will we offer food according to cues? Which two real choices are available? How will we ask for relief and repair? Keep it beside support contacts, not as a judgement or a catalogue of techniques. Review one item each week, because changing everything at once makes it impossible to learn what helped.
An environment cannot control a child. What it can control is the quality of adult response: less unnecessary stimulation, safe limits, clearer observation and an exit when someone reaches capacity. That is the point of five decisions made beforehand: meeting difficulty with a shared route rather than an impossible promise of perfect calm.
Practice before the emergency#
To keep the card from becoming decoration, the family can rehearse it on a calm day: act out arriving home, identify where sound can be lowered, locate contacts, and decide which adult can say “relief” without a long explanation. Rehearsal reveals gaps under little pressure. It also shows that the five agreements must fit age, culture, health, disability, work schedules and the available network. When a decision does not help, change the environment; do not blame a child for failing to fit the plan. An honest review can ask who is always expected to be available, which transition depends on one adult, and which sounds cannot realistically be removed. A household may not create a silent evening, but it can prepare one lower-stimulation area, keep water ready for the tired caregiver, reserve a safe feeding chair, and display the handover words. Grandparents, friends and child-care helpers do not need to copy every detail. They need the safety limits, the relief signal, and the knowledge that crying does not prove anyone has failed. After an episode, retain what reduced tension and remove what only added urgency. The card then becomes a shared learning tool rather than a contract to control behavior.


